
It is the client who knows what hurts, what directions to go, what problems are crucial, what experiences have been deeply buried.
Carl Rogers’s advocacy of the client as a self-healing organism is a brilliant riposte to the authoritarian, expert-directed therapies of the early twentieth century. And that trust in the client’s inherent capacity for healing, growth, and self-direction remains at the heart of contemporary understandings of the person-centred approach. One thing that is not entirely clear from Rogers’s quote, however, is the question of ‘How much?’ That is, To what extent does the client know what hurts and what direction to go? Is it totally, or to a great extent, or mostly-but-not-always? Similarly, when Rogers states that individuals have within themselves ‘vast resources’ for self-understanding and for altering their behaviours, does he mean that they have it all, or vast but not everything? And that’s a limitation in the wider person-centred literature too. For instance, when Susan Stephen, in the 2024 Handbook of Person-Centred Psychotherapy and Counselling, defines nondirectivity as, ‘an attitude held by the therapist from which they trust and relate to their client as a person with agency, autonomy and the capacity to grow…’ how much trust are we talking about here? Does this mean trusting that they will grow without any external input; or trusting that they have the capacity to grow given particular external circumstances (e.g., the six Rogerian conditions); or trusting that they are oriented towards growth, but not necessarily always capable of realising it themselves. After all, most therapists, whatever their orientation, would say that they trust their clients and believe in their agency and autonomy to some degree. So does that make CBT therapists, or EMDR therapists, also nondirective? Where do we draw the line?
This issue is more than just semantic. Many of the current debates around person-centred practice relate to the degree of therapist involvement that there should be, and what form that should take. If we hold that all the answers lie inside the client, then that would suggest therapists should adopt a role that closely follows the client’s tread (for instance, the ‘empathic unfolding response process’ described by Beth Freire). But as we move towards a less absolute trust in the client’s capacity for self-healing, so the role of therapist input—above and beyond the client’s own natural process—becomes more justified.
An absolutist understanding of the client’s self-healing capacity—that all wisdom and knowledge lies inside—is appealing on several fronts. It gives us a clear, straightforward, and directly applicable understanding of what clients want and need and how to practice. And, perhaps, it also provides the ‘dopamine hit’ that all neatly definitive answers give. For those of us who want to engage with clients in deeply respectful and valuing ways, it also privileges the client in a unique manner. And yet, in this blog, I want to argue that such an absolutist position—in contrast to a more graded, nuanced one—is problematic on a range of fronts.
1. If all the answers are within the client, why do they need therapy?
It’s the most obvious critique of an absolutist position: if a client knows, totally, what heals and what hurts, what’s expressed and what’s suppressed, then what is the point of therapy? Surely, the client, on their own in their own good time, would find out all the answers they need for themselves—grow in the best way possible. In response, one might argue that clients have those answers deep within, but then have learnt to suppress them due to external forces. What this doesn’t explain, though, is why they would do that? Surely an organism that knew everything about how to self-heal wouldn’t then suppress that knowledge. And if you go so far as to say that people are forced to by their environment to suppress their own deepest knowledge then, as Rollo May argues, you’re left with the conceptualisation of an organism that is malleable, passive, and susceptible to being controlled—again, what we’re left with is the question of why a self-healing organism would be so. If we are providing therapy, we have to believe that, at least to some extent, there is something that clients need that they don’t already have.
2. It can’t explain why people experience psychological difficulties
Along very similar lines, if we say that people have within themselves all the resources to heal, then why do people experience psychological difficulties at all: why phobias, or depressive episodes, or addictions? How can an entirely self-healing being go ‘wrong’? One answer might be that these experiences and behaviours aren’t wrong, they’re actually an expression of that self-healing tendency—they just seem unhelpful from the outside. But then, for these clients themselves, such problems are often perceived as very wrong, and as something they want to be rid of; so if we trust the client, we have to trust their sense of wrongness. We might also say that the client is absolutely self-healing, but that the environment turns the person against themselves. Again, though, we then come back to the problem of why a self-healing organism would do that. At some point, in some way, there needs to be an acknowledgement that the organism, even with the best will in the world, can sometimes do things that aren’t in its own best interests.
3. There’s no evidence for it
From such fields as ‘self-determination theory’ and social psychology, there’s some fascinating evidence to suggest that people have a natural tendency to move in the direction of growth, healing, and self-integration. A study by the brilliant humanistic psychologist Kenny Sheldon and colleagues, for instance, showed that participants tended to move towards intrinsic goals and/or away from extrinsic goals over periods of time. A summary of all the evidence that supports the self-healing capacities of clients is presented in Bohart and Tallman’s classic 1999 text, How Clients Make Therapy Work: The Process of Active Self-Healing. Another great source of evidence is The Heroic Client, by Barry Duncan and colleagues. But showing that clients have a remarkable capacity, at times, to self-heal, is very different from showing that clients have everything, always within them to heal themselves. For that, to the best of my knowledge, evidence is entirely absence. That means, then, that an absolutist belief in the human capacity for self-healing is much more a matter of faith than evidence-based actuality.
4. It’s inconsistent with established developmental theory
If you consider the most basic theory of development, in the work of Jean Piaget, you see a model of human growth that combines processes of both assimilation and accommodation. Assimilation is the process where the child fits new information into their pre-existing schema. That process could be compatible with the hypothesis that all wisdom lies inside: the child uses what they already know to make sense of their world. But then the other side of the coin is the process of accommodation, where the child is adjusting their schema to incorporate new, and potentially contradictory, information. So, in Piaget’s model, there is learning from outside as well as inside—and, no doubt, that can include pathways and strategies to health. In response, one might say that the inner self-healing drive is not knowledge, per se, but our capacity to engage with the world in self-healing ways. For instance, it’s not that we know, intuitively, that apples are healthy, but a child’s positive response to eating an apple reveals their inherent inner tendency towards growth: the ‘organismic valuing potential’. And, similarly, you could argue that a person senses, intuitively, that such psychological practices as meditation, or yoga, or psychoeducation are good for their mental health. The problem here, however, is that the ‘outside’ becomes so integral to what is considered ‘inside’ that it no longer really makes sense to say that all wisdom lies within the person. Knowledge about yoga, or meditation, or psychoeducation add something that wasn’t there before. There is a learning, something more is added: and the value of learning, from the outside, mitigates against a wholly absolutist view of inner self-healing.
5. And people really do benefit from external learning
If you look at the evidence on psychological methods like psychoeducation, or teaching clients mindfulness, or dialectical behavior therapy (DBT) input on mentalising skills, there’s no doubt that clients can benefit from learning new things. Quantitative controlled studies show that (e.g., here), and so do qualitative study, which directly ask clients about what they found helpful in therapy (e.g., here). Indeed, ironically, when we asked young people what they found most helpful in person-centred therapy, they themselves said that it included learning new techniques and strategies for managing anxiety and interpersonal problems (see here). Again, this isn’t to go to the other absolutism and suggest that all self-healing, instead, comes from outside. What the psychotherapy research shows is that both attending to inner processes, and learning from the outside, facilitates the healing process.
6. thinking in binary terms contradicts a person-centred appreciation of nuance and complexity
From an absolutist standpoint, either you believe in the self-healing capacity or you don’t. Wei Tao Ong and colleagues, for instance, argue that the ‘the person-centered approach has a distinct anthropological, epistemological, developmental psychological position which cannot be combined with any other orientation’, based on an, ‘underlying image of the human being as a proactive person driven by the actualizing tendency, such that clients are trusted to be their own best experts.’ As another example of a binary conceptualisation, Andy Hibberd writes on Counselling Directory, ‘Therapy can broadly be split into two types: the therapist either believes they are the expert, or they believe you are’, and goes on to states, as with Ong et al., that person-centred therapy is uniquely of the former type. This ‘person-centred exceptionalism’ is depicted in Figure 1, where a conceptualisation of the client as self-healing is contrasted against a belief in therapist expertise as healing. Here, there is no middle ground.

Figure 1: Binary Conceptualisation of Self-Healing Beliefs
But such a bifurcation betrays what, I imagine, is a much more complex, nuanced, and graded reality, where therapists’ beliefs about clients’ self-healing capacities lie on a spectrum, ranging from absolutist beliefs at the self-healing extreme to absolutist beliefs at the therapist-as-healer extreme. And I do say, ‘I imagine’ here, because, of course, this is an empirical question, and it may turn out, if someone researched it (and what a great project to do!), that there are two entirely distinct sets of beliefs. But my strong prediction would be of a distribution much closer to Figure 2, with all of us placed along a spectrum, with variations both within and between orientations (and also with different clients at different points in time, see below). Certainly, in my experience, I’ve yet to meet a CBT or psychodynamic therapist who believes that the client has no role in their own healing. And, if they did, they would have to be pretty ignorant of the psychotherapy research evidence, showing all of us that, whatever our orientation, that it is the client who tends to be the hero of the therapeutic drama: the principal driver of therapeutic change.
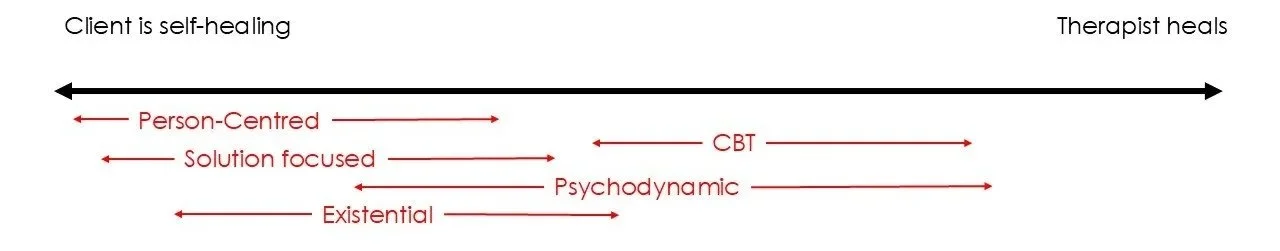
Figure 2: Gradated Conceptualisation of Self-Healing Beliefs
7. its extension to biological processes get seriously problematic
The organism, from a person-centred perspective, is a biological entity as well as a cognitive one: a cognitive-affective-somatic whole. So if we’re saying that the organism is absolutely self-healing, we also need to extend that to its biological capacity to heal from unwellness and disease. Now, again, a graded position can recognise that the body has enormous capacity for healing itself: for instance, that our liver self-repairs, or our immune system has a remarkable capacity for fighting off viruses. But the absolutist position, that the body has, within itself, everything it needs to maintain health, moves us into the grounds of medical non-interventionism: that no external treatments, no vaccination programmes, no medications, no surgeries are necessary for physical wellbeing. Here, again, the person-centred approach moves into the territory of faith: like, for instance, the Christian Scientists who avoid medical care and rely on spiritual healing only. And, indeed, a therapist who holds an absolutist self-healing stance, who withholds potentially helpful advice or suggestions from their clients when requested (for instance, on how to find housing support) might be likened to a medical non-interventionist who denies themselves or their family external care. Put conversely, to the extent that we accept the value of medical intervention—at certain times, in certain instances—we recognise that sometimes an organism’s natural healing capacity needs help or support.
8. it runs into contradictions when you consider client preferences
The paradox of putting total trust and faith in the client is that, in fact, the majority of clients express a preference for advice, guidance, and suggestions from their therapists—they want therapist directivity (see, for instance, here). So if we trust the client fully, that means trusting that, for many clients, we should be providing external input; meaning that we don’t totally trust that they have, inside, all the knowledge and wisdom to self-heal! In response, one might say that clients only want external help because they’ve been conditioned to an externalised locus of evaluation: it’s not an expression of their deepest, most authentic organismic being. But, again, we’re left with the question of why an absolutely self-healing organism would allow itself to be conditioned in that way. Moreover, if we’re saying that we don’t trust clients to know what is self-healing for themselves, that is hardly much of an expression of trust: indeed, we’re putting our own therapist expertise (about their self-healing capacity) before the client’s own self-expressed knowledge and wisdom. So, either way, an absolutist position on self-healing falls into contradiction.
9. it’s inconsistent with contemporary feminist and multicultural perspectives
Today, many contemporary feminist, multicultural, and other postmodern and radical perspectives reject the idea that the organism is a separate, distinctive monad. Rather, they see human beings as embedded in a relational nexus: inherently and unavoidably intertwined with the people and culture around them. So, from this standpoint, there is no distinctive ‘inside’ where all knowledge and self-healing capacity can reside. Rather, knowledge and wisdom exists in an interpersonal and social field. From a multicultural perspective, this includes the wisdom and understanding of indigenous cultures: for instance, as healing practices or as activities that bring the community together.
10. Diversity across clients
Finally, if we simply hold that all clients have within themselves all they need to self-heal, then we’re also not acknowledging that clients’ may have these capacities to different levels. It becomes a generalised, one-size-fits-all understanding, rather than being open to potential differences in the people we work with. And this, again, would seem to contradict the fundamental principles of a person-centred approach, with its deep appreciation of human uniqueness and diversity.
Implications
Moving from an absolutist position on self-healing to a more graded one, even if we land far towards the self-healing end of the spectrum, may seem like a small shift, but it has important implications for how we think about therapy and the person-centred approach.
First, it means that we need to find deeper and more sophisticated ways of conceptualising what we mean by the self-healing capacity, or related terms like the actualising tendency. Here, it’s no longer enough, as with the binary model, to say that we believe in clients’ capacities to self-heal. Instead, we need to specify what we mean by this: to what extent, under what circumstances, how might it function in suboptimal ways, and what external input may sometimes be needed? What do we trust in our clients and where might we be more willing to challenge? In other words, once even a small chink appears in an absolutist standpoint, it behoves us to them develop our psychological models to explain how and why this might arise. In my own writings, for instance, I’ve argued that people are inherently directional beings—always striving towards intelligible and meaningful goals—but that we don’t always know the best ways of getting there. So although, from this standpoint, it is the client who ultimately knows what they want and need, there are also things that they can learn about how to best progress towards those ends. This is just one understanding with, of course, it’s own challenges and limitations, but once we shift—even slightly—from an absolutist position, it’s the kind of critical thinking needed to maintain a coherent understanding of the person.
Second, by moving to a more graded position, even if slightly, we put ourselves more on a par with other therapeutic orientations, and this opens up the door towards greater integration and co-thinking with other approaches. No longer is the person-centred approach so special, unique, and exceptional—as it is in the binary conceptualisation. Rather, it means that we need to acknowledge that, in fact, lots of other therapists also recognise and respect client strengths, and that we can talk to, learn from, and build with their understandings. For instance, we can look at the work on the heroic client (from a solution focused background), or the activation of client strengths (from a psychotherapy research stance).
Third, in practice, it means that we can allow ourselves to consider the role that our own input and expertise might have for clients. Not every client all of the time, but if we recognise that we can have some role in facilitating the client’s healing journey, it raises the question for us of when and where and how. And in what ways do we want to contribute: for instance, through learning CBT methods, or training in EMDR, or bringing in attachment theory. In my experience, person-centred trainees often feel that such skills and understandings are ‘off limits’, extrinsic to a purely person-centred way of approaching clients and practising. But if we see person-centred practices as a constantly nuanced, flexible process of attending to the client—prizing the client’s wisdom—while also bringing in our own knowledge and expertise, as and where appropriate, we can start to see such integrative as the very essence of what it means to practice in a person-centred way.
Conclusion
I’m sure one challenge to this blog will be that the absolutist position I’m critiquing is a straw man: that, in reality, no person-centred therapist actually holds such a stance. And, indeed, I imagine that, in practice, that is actually the case. In our own research, we’ve seen how person-centred therapists utilise a variety of methods, including psychoeducation and teaching relaxation exercises, to optimise their helpfulness to clients. But, in terms of explicit theory, literature, and training, there is often a chronic under-specifying of what terms like ‘self-healing’ or ‘actualisation’ actually means. Even with Rogers, as with the opening quote, such terms tend to be presented in an implicitly binary way—that person-centred approaches believe in the client’s self-healing capacity, in contrast to other orientations—rather than a deeper and richer conceptualisation of what this means. In fact, my sense is, for some members of the person-centred community, a belief in the ability to externally facilitate a client’s healing in a range of proactive ways is something of a ‘dirty secret’: a practice they do but don’t talk about or feel is compatible with their training. And if it’s outside of training or theory, or even outside of consciousness, the danger is that there’s then a lack of reflexivity and deliberative use of these skills. If we acknowledge, for instance, that psychoeducation can play a positive role in person-centred practices, we should be discussing what kind of psychoeducation, and when, and how.
More than anything, then, this blog is a call for person-centred clinicians, trainers, writers and other members of the community to specify what they mean by the client’s capacity to self-heal, or to actualise. What actually is this, and to what extent are they saying that that capacity is there? If they feel that that self-healing capacity is absolute, fair enough, but then the challenges presented above do, I think, need to be addressed. At the very least, they need to ask, ‘What is it that I am doing with a client if the client has all the resources within, and how does that make sense?’
So just to be absolutely explicit, again, the point of this blog is not to argue against the client’s self-healing capacity: it is something I have passionately advocated all my career. Indeed, it’s probably because I am so passionate about empowering clients that I feel it does them a disservice not to have richer, more complex, and more nuanced understandings of their potential for change. The point, rather, is to critique an absolutist understanding, and to suggest that a more graded conceptualisation is both truer to what most of us actually think and feel, and also opens the door to deeper and more sophisticated conceptualisations, research, and practice. Recognising that it is not all-or-nothing, and that different clients may differ in their capacities to self-heal, means that we can respond more fully to the client in front of us, and also evolve as a person-centred orientation towards more fitting, meaningful, and sophisticated forms of theory and practice.
Acknowledgements
Photo by Grooveland Designs on Unsplash