Preferences

Preferences in Person-Centred Therapy: Should We Ask Clients What They Want?

From a person-centred standpoint, should we be asking clients about their preferences for therapy: for instance, the concerns they’d like to talk about, the style of therapy they want from us, the goals they’re keen to work towards?

It’s a complex question, but an important practical one, and it highlights some of the areas of constructive difference between a pluralistic and a more classical approach to person-centred therapy.

Let’s start with areas of agreement. First, if a client expresses a preference, therapists of any person-centred persuasion (indeed, therapists of most persuasions) are likely to try their best to accommodate it. Second, across both these perspectives, therapists are likely to only offer options that they, themselves, can accommodate. That is, for instance, no one is going to be asking a client if they want EMDR or psychoeducation on sleep hygiene if they, themselves, don’t have those skills and competences. Knowing what we can actually offer—being authentic—is the first step in any preference work.

Where things start to differ, though, is around the question of whether therapists should broach the issue of preferences: that is, proactively asking a client what they might want. Is it appropriate, for instance, for a therapist to ask, ‘What would you like to explore today?’ at the start of a session, or to say to a client, ‘We could explore your feelings to your mother through talking about them, or having a go at expressing them out loud, what would you prefer?’

From a classical standpoint, things emerge naturally, and there is no need to rush the process. Indeed, if we start to probe and ask clients what they want, we may get responses from their conscious, presentational self, rather than from the deeper, and potentially more hidden, elements of their organismic wants and needs. The figure below provides a very simple model of person-centred theory. Here we have the person’s/organism’s actual experiencing, areas A + B, of which B is what they experience and can acknowledge, and A is what they experience but can’t acknowledge. And then we have area C, which are the things that the person thinks they experience, but actually doesn’t. So, for instance, a client thinks that they want CBT techniques because they’ve heard from their friends or social media CBT really works. But maybe, for them, those CBT techniques would actually be really frustrating, or unhelpful. This puts the desire for CBT techniques in area C and, if a therapist then asks the client their preferences—particularly towards the start of therapy—they may end up with responses that bear no reality to what a client actually wants or needs (areas A and B). From this standpoint, what’s essential is to give the organismic experiencing, the growth process time: when clients are ready to ask for what they want, it will emerge—naturally, organically. And no therapist direction is needed: because if the therapist starts to suggest X, or Y, or Z as possibility, it’s going to take the client even further away from their actual organismic wants and needs towards something that, for instance, is there just to please, or conform to, the therapist.
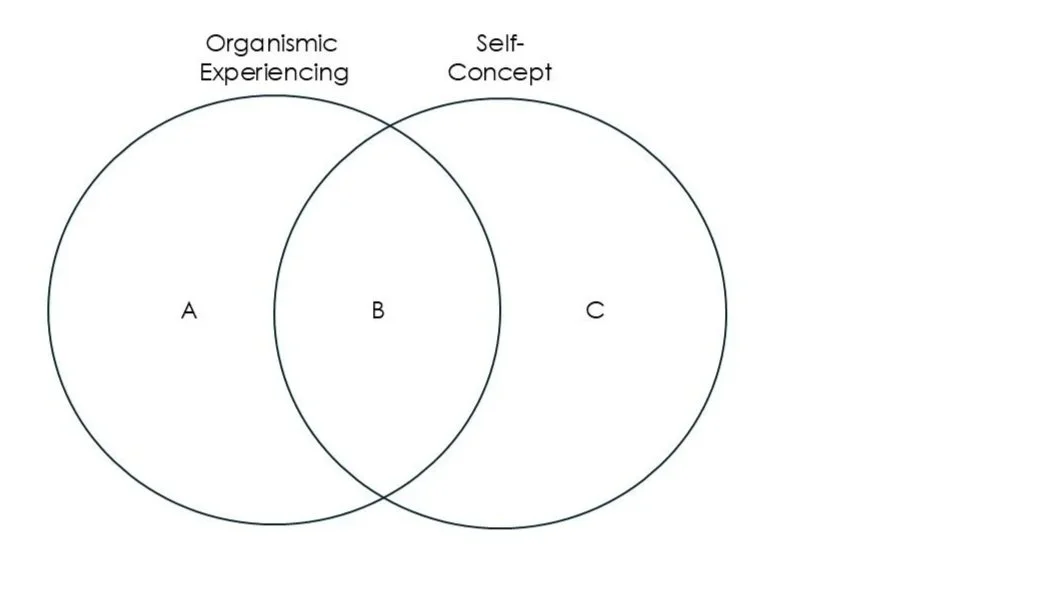
Person-Centred Model of Organismic Experiencing and Self-Concept

That all makes eminent sense but, for me, there’s also challenges with it. First, and perhaps most importantly, from a contemporary postmodern perspective (i.e., that everything is socially constructed) the assumption that there is some ‘neutral’ way of doing therapy would be seen as something of a myth. That is, whether the therapists asks the client their preferences or not, the therapist is still always doing something, still responding in some way, and what they are doing may or may not match what the client’s actual preferences are. Typically, for instance, a person-centred therapist will be engaging in an empathic, accepting, and congruent way. Great… but that is doing (or being) something, it’s engaging in a particular manner, and that may or may not align to what the client is looking for. So if you proactively ask clients their preferences, there’s the potential for preference mismatch, but if you don’t ask there’s also potential for preference mismatch: not asking is not going to just mean that everything is automatically aligned.

As a counterargument, one might suggest that what all clients want and need, most deeply, is an empathic, accepting, and congruent relationship. However, that becomes even more problematic, because then the therapist is saying that they know, most fundamentally, what the client wants and needs, even if the client does not know that themselves. So the therapist, here, is effectively adopting an expert position in a way that threatens to fundamentally undermine the client’s autonomy and sense of self-control: ‘I don’t need to ask my clients their preferences because, ultimately, I know what they need better than they do themselves.’ Again, the point here, from a pluralistic standpoint, is the ‘meta’ one: that a therapist of any orientation, person-centred or otherwise, always holds a position, always has some stance. And once you recognise that, the issue is not whether or not the therapist imposes a choice on the client, but whether or not the client has some choice in relation to the therapist’s pre-decided way of being. If not, if no choice is offered, then that’s less simply allowing the client’s organismic tendencies to emerge; and more ‘imposing’ on the client, in an unreflective way, the therapist’s own choices about what’s right in therapy.

This issue, perhaps, becomes more acute in an era when therapy is often time-limited. With infinite time, the client’s own inner actualising tendency can, perhaps, fully unfurl. There is no need to introduce choices, because the client will come to them naturally themselves. But what if a client has only six sessions, or 12? Then, there are fundamental limits on what is possible, and a therapist’s choice to be one particular way is likely to mean that a client won’t have choices for something else. Again, it comes back to the point that there is no neutrality: if you offer a client, for instance, some relaxation techniques, that is influencing them in some particular way. But, over the course of 12 weeks, if you don’t offer relaxation techniques, that is also influencing in some way—albeit through absence rather than presence.

As a counterposition to this, it could be argued that if a preference didn’t come from the client’s ‘inside’, maybe it wasn’t meant to be. Here, I think classical and pluralistic approaches also tend to have different views of where wisdom is ‘located’: individually, or in the client’s relational field. From a classical standpoint, everything that needs to be known is there, within the client, so why bring in anything, any options, from outside? But if wisdom is relational, then there may be things that the client doesn’t know that may be of genuine healing to them. Here, therapists have the potential to offer options that may be meaningful and valuable, above and beyond what is already in the client’s organismic potential.

Another counterposition from a more classical standpoint: therapists don’t need to ask, explicitly, about clients’ preferences because if they are meeting the client deeply, then they will intuitively sense what it is the client wants and needs. Again, I think there’s a lot of truth in this supposition: through a deep embodied empathy, it is remarkable what can be sensed and intuited in clients. And research, for instance, on mirror neurons shows robust neurocognitive grounds for such processes. And yet, from the psychotherapy research, we also know that therapists’ and clients’ experiences of the therapeutic process, within the same dyad, can be markedly different. For instance, in our own research on relational depth, we found times when therapists (person-centred) experienced a depth of connection with their clients that was very mismatched to the clients’ own experiencing. Overall, the level of matching was actually quite high, but that certainly wasn’t always the case, and this was as much in experienced therapists as trainees. As therapists, then, while we can learn much of what clients want and need from trusting our own intuitive sense of it, from a pluralistic perspective we should never rely on only one source of ‘truth’. Explicit, as well as implicit, conversation would be indicated to develop a more triangulated understanding of what the client wants and needs.

In terms of finding ways forward beyond this dilemma, some thoughts come to mind.

First, being upfront with clients about the way we work is a means of practising from a particular standpoint while minimising the extent to which this might be an imposition on clients. If, for instance, we describe to clients what we do from our classical standpoint—how it’s a space for clients with empathy and acceptance, where they can grow at their own pace, where we won’t be introducing or enquiring into preferences—then it gives clients more power to either choose it or choose against it and look elsewhere. Yes, as a therapist we are still holding a position, but it is a position that is explicit, that clients can see as our position, rather than a truth, and in that sense we’re minimising our power over.

Second, might be the importance of recognising that clients can really vary in how much they want therapists to introduce and ask about different options, and individualising in this way can capture the value of both classical and more pluralistic approaches. From an initial dialogue, for instance, it might become evident that clients really want space in therapy to grow at their own pace without much involvement from the therapist, or it might become clear that they would really appreciate the therapist’s regular check-ins on where they want to go. Of course, the problem here is that to find this out may require initial questions about the client preferences (about preferences), which then gets us back to the issue of whether we should be asking clients what they want or not in the first place. If we believe that wants and needs should be allowed to emerge at their own pace then, by definition, we’re not going to be asking clients what their wants and needs are for that process.

Third, research might be helpful here, asking clients what works for them in terms of these kind of preference discussions. We did a qualitative study of this type and got some interesting initial findings: seeing the range of different responses to preference work, and how it could be experienced as both helpful and not. Again, though, such research could be critiqued on the grounds that participants’ responses are going to come from their self-concept rather than their organismic experiencing (area C), and in that sense not to be trusted. If a client is saying that they valued expressing their preferences, for instance, is that because they want to be liked, or feel obliged to comply with the researcher?

Whatever positive way forward we find here, it’s likely to be in the nuances and complexities, and away from black and white generalisations. It’s true, for sure, that clients can express preferences that don’t genuinely match what they want or what helps them, but it’s also not true to say that that is always the case. Clients can know, and articulate, preferences that are of deep meaning to them, and they can also experience the process of being asked about preferences as deeply empowering. But some can find it disempowering, or even shaming if they don’t know what they want. And, most likely, preference work is not a binary thing (either we do it or not). Also, there may well be a plethora of times in our work when we are, explicitly or not, inviting clients to express and follow preferences. A simple reflection, for instance, like ‘It sounds like you were really hurt by what your mother said,’ may invite a client to consider whether they want to talk more about that hurt or not. The differences across person-centred approaches, then, are likely to be in emphases, in subtleties, in touches of more or lesser ways of explicating. For me, personally, I think it is a willingness to sit with the wholeness of that complexity, and to ask and explore these complex questions, that expresses the essence of what being person-centred means.

Acknowledgements

Photo by Sophia Kunkel on Unsplash

Note

This is something for a future blog but, in many ways, I think the Figure above (with the two circles) can help us make sense of some of the core tensions between classical and more pluralistic approaches to person-centred therapy. A classical approach puts emphasis on A and B, what is organismically there. It trusts that this will emerge, and wants to support the wholeness and authenticity of the individual coming into being. But the problem is, in doing that, it may mean not fully ‘trusting’ what is presented by the client in B (and C): it means looking, potentially, ‘past’ the person in the room with you, and thereby becoming the expert in the room, who knows what the client wants and needs beyond that client’s own understanding. By contrast, a pluralistic perspective tends to emphasise more trust in the client as they are in the room in the here-and-now: the person in front of you. So it’s not about trying to look at who they ‘really’ are, what’s ‘behind’ them, but a respect and valuing for the person then and there, and a trust in their choices and preferences, as they are now. Problem there, though, is that can then over-emphasise the conscious at the expense of what is not stated or known by the client. These aren’t, of course either/or alternatives: ideally we trust both aspects of the client—actuality and potentiality—but there’s inevitably going to be times when these trusts are pulling in different directions: like, for instance, whether we think it is of value to ask the client, in the here-and-now what it is they’re wanting from the therapeutic process. So when we talk about trust in the client’s autonomy, what do we actually mean by the client? Do we mean the person presenting in the room, or do we mean the person they can be? And we might say, ‘Well, obviously, all of this,’ but then what if these ‘parts’ are pulling in different directions? These are, again, complex questions, with no easy answers, but through respectful in-depth dialogue across positions we may, perhaps, be able to move forward to deeper understandings.
Using Research Evidence to Predict and Optimise Therapeutic Benefit: A Multilayered Approach

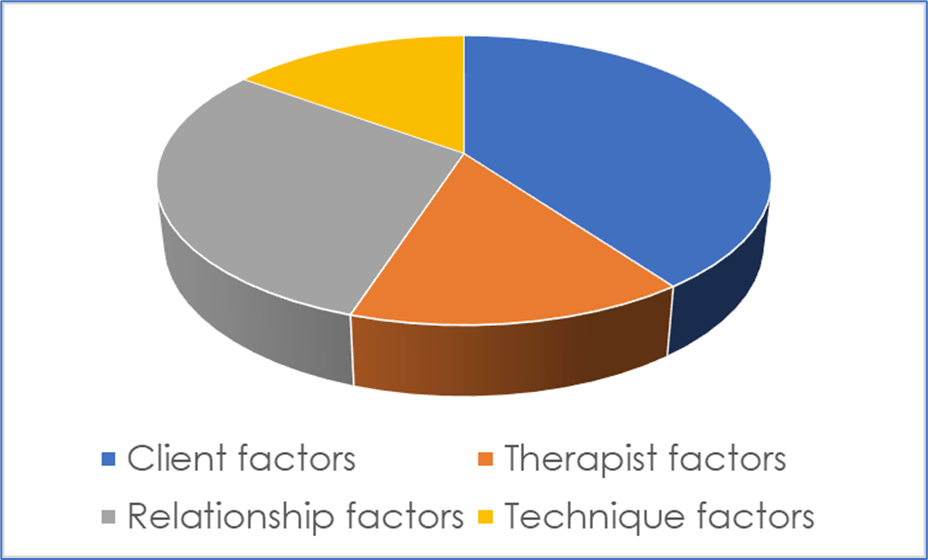
How can we use research data to inform and improve therapeutic practice? When I wrote my book Essential research findings in counselling and psychotherapy (Sage, 2008), I did what most writers in the field had done: I tried to organise and make sense the evidence by different ‘factors’. I used the usual suspects: client factors (e.g., the client’s motivation); therapist factors (e.g., the therapist’s gender); relationship factors (e.g., the amount of goal agreement); technique and practice factors (e.g., using two-chair work); and orientation factors (e.g., working in a person-centred way). That gave a fairly simple and clear taxonomy and meant that it was possible to describe the relative contribution of different factors to therapeutic outcomes. For instance, one might estimate, based on the most recent evidence, that approximately 40% of variance in outcomes is due to client factors; 30% due to the relationship; 15% to therapist factors; and 15% due to the particular techniques, practices, or orientation used. This can then be neatly depicted in a pie chart, like Figure 1.

Figure 1. Illustrating the Contribution of Different Factors to Therapeutic Change

Despite its clarity, organising research evidence in this way has its limitations. One very obvious one is that it implies that each of these factors is discrete when, of course, they are likely to inter-relate to others in complex, mutually reinforcing ways. Another problem, more directly related to the framework developed in this article, is that they tend to infer that each client is influenced by each of these factors in the same way and to the same extent: that relationship factors such as empathy, for instance, lead to 30% of outcomes for Client A, and also for Clients B, C, and D. The reality, however, is that Client A may do very well with empathy while Client B may not; and while relationship factors may be essential to Client C’s recovery, Client D may do very well without them. Indeed, much of the cutting edge research in the psychotherapy field—by leading figures such as Zachary Cohen and Jaime Delgadillo—is on the particular factors that lead particular clients to do particularly well in particular therapies; and the algorithms that can then be developed, based on such evidence, to optimise benefit. Organising the evidence by factors may also limit its utility for therapists. As practitioners, we do not tend to think about our work, systematically, in terms of these different factors (e.g., ‘What can I do to improve myself as a therapist?’ ‘What can I do to improve my relationship?’); and it is also important to note that different factors may have very different implications for practice. Knowing, for instance, that clients with secure attachments do better in therapy than those with insecure attachments (a client factor) does not really tell us anything about how to work; while knowing that clients tend do better when their therapists are warm and genuine can have important implications for practice. So although these factors, in Wittgenstein-ian terms, have a ‘family resemblance’, they are actually quite distinctive things.

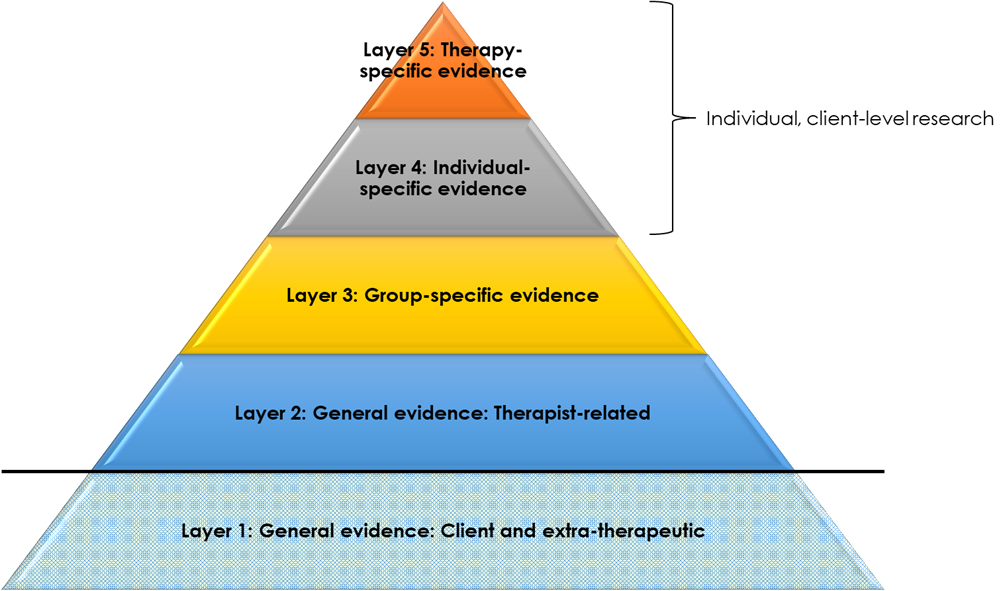
The aim of this article, then, is to describe a way of organising and conceptualising therapy research evidence that addresses some of these problems: allowing for a more nuanced, comprehensive, and personalised conceptualisation of data; and potentially more useable by therapists. The essence of this framework is a pyramid (or funnel, see Figure 2), with different layers of evidence at increasing degrees of specificity and proximity to the client. Each layer builds on the previous ones: from research evidence that is relevant to all clients to research evidence that is specific to a particular client in a particular session. As this pyramidal form suggests, as we move upwards, evidence may become more sparse. However, because of its greater specificity, and because it is most proximal to clients’ actual experiences—such evidence may be of greatest value. For instance, research suggests that clients generally do better when therapists are empathic (Layer 2), but if evidence exists that the opposite is true for highly paranoid clients (Layer 3), then the latter finding would tend to take precedence to guide practice with a highly paranoid client. However, if it was then established that, for a particular highly paranoid client, they had a strong preference for an empathic therapist (Layer 4), then this higher-layer evidence would take precedence over the group-specific (Layer 3) finding.

Figure 2. A Pyramidal Framework for Organising Therapy Research Evidence

The foundation of the pyramid, Layer 1, is general evidence on client and extra-therapeutic factors that tend to determine good outcomes. For instance, clients who are psychologically-minded tend to do better in therapy, as do clients with more social support. These factors are separated off from other factors (depicted in Figure 2 by a dividing line), because they are less relevant to what therapists do. Rather, they are the grounding—to a great extent outside of the therapist’s control—as to how therapy is likely to proceed. In this respect, these general factors have an important role in predicting outcomes—and, indeed, may explain by far the largest proportion of variance—but do not have much role, per se, in informing or shaping how therapists work.

Note, the term ‘tend to’ indicates that, while these findings are drawn from generally representative samples (or samples assumed to be generally representative), this is not to suggest that these factors will be true for each and every client. Rather, this is evidence, across all clients, of averaged tendencies, around which there will always be considerable group-, individual-, and session-layer variance.

Building on these general client and extra-therapeutic factors are general factors that are related to the therapist and their therapy (Layer 2). This includes therapist factors (for instance, therapist gender), relationship factors (for instance, the alliance), and technique factors (for instance, use of cognitive restructuring). These are findings that reach across all clients and, although still averaged trends, can be very useful for therapists to know. In the absence of any other information, they provide a useful starting point for work: for instance, be empathic, listen, or self-disclose to a moderate extent.

At a greater layer of specificity (Layer 3) is evidence of particular factors that tend to be associated with helpfulness for particular groups of clients. By far the greatest amount of evidence here focuses on clients grouped by particular mental health diagnoses—for instance moderate depression or obsessive-compulsive disorder—as reviewed and operationalised, for instance, in National Institute of Health and Clinical Excellence (NICE) guidelines. Considerable research is also now available on clients with particular cultural identities (e.g., people of colour, lesbian clients), and what tends to be most effective for them. There is also a wide range of research on other ‘aptitude–treatment interactions’ which identifies the factors that tend to be most effective with particular groups of clients. For instance, clients who are more reactive tend to do better in less directive therapies, while the reverse is true for clients who are more compliant. Of course, clients may be members of multiple groups—‘intersectionality’—such that practices indicated may be complex or, potentially, contradictory. Tailoring therapies to particular client characteristics is what Barkham terms ‘precision therapy’, linked to the wider development of ‘precision medicine’: ‘predicting which treatment and prevention strategies will work best for a particular patient’ (NHS England).

Moving up in specificity, to Layers 4 and 5, entails a shift towards individual-level research and data gathering (Figure 3). This is, perhaps, the most important and novel part of the framework being suggested here, because a continuum is being proposed from (a) general- and group-level research to (b) contemporary, individual-level monitoring: one segues into the other. In other words, the framework suggests that what researchers do ‘in the field’ is not so different from what therapists do when they are working with individual clients using routine outcome monitoring (ROM): it is all part of one broad spectrum of using data to help inform practice. This may be helpful for practice because it de-mystifies ‘research’ and puts it on a equal footing with things that a practitioner would typically do. Now, research about populations or groups is not something that researchers do far away on some other planet, but is an extension (broader, but less specific and proximal) of what therapists are, actually, doing all the time. That does not mean it can be waived away, but it does mean that it can be considered a friend rather than enemy (‘the facts are friendly’, as Carl Rogers said).

Describing individual-level data gathering as ‘research’ is a somewhat unusual extension of the term. Almost by definition, ‘research’ is seen as involving generalising from specific individuals to the wider group or population. However, if research is defined as ‘a detailed study of a subject, especially in order to discover (new) information or reach a (new) understanding’ (Cambridge Dictionary), then generalisations can also be at the individual client layer: from, for instance, one session to another, or from assessment to across the course of therapy as a whole. Individual-layer research like this is not something you would see published in a journal, nor could it be summarised in a book like Essential research findings. Even with individual-focused research methods like autoethnography or heuristic research, the aim is to reach new understandings that are of relevance across clients or contexts. But with the individual client-layer research described here, the aim is solely to use data to reach new understandings about this individual client. It is a form of systematic enquiry which the therapist, themselves, does, to help optimise their therapeutic work with the client by drawing on data.  

Figure 3. Individual Level Research

Layer 4, like Layer 3, entails the use of data, prior to the commencement of therapy, to estimate what is most likely to be helpful for a client. While Layer 3, however, makes such assumptions on the basis of group characteristics, Layer 4 focuses exclusively on that client’s individual uniqueness. This is the complex, rich mixture of characteristics and experiences that make the person who they are: irreducible to any particular set, or combination, of group characteristics. In terms of system theory, this is their ‘emergent properties’; in terms of the philosopher Emmanuel Levinas, their ‘otherness’. Understanding how data at this layer may be captured and integrated into therapy is, perhaps, the least well-developed element of this framework. However, one notable and well-researched element here is the client’s preferences: recorded, for instance, on our Cooper–Norcross Inventory of Preferences (C-NIP) at assessment. The focus of such individual layer research, then, is on what this specific client needs and wants from therapy; and the incorporation of such findings into the therapeutic process.

Finally, at the highest layer of specificity (Layer 5), is the use of data to guide the ongoing process of therapy, as in the well-researched and -developed practice of routine outcome monitoring (ROM). In ROM, the therapists uses data from ‘outcome forms’ (like the CORE-10 or PHQ-9), and potentially also ‘process forms’ (like the Session Rating Scale), to track how the client is doing, and to try and adjust the therapy accordingly. For instance, if the client’s layers of symptoms are worsening, the therapist may draw on pre-specified ‘clinical support tools’, such as a protocol for reviewing the therapeutic alliance with the client. In this way, ROM can be considered research at the highest layer of specificity: generalising from data captured at particular points in therapy (for instance, at the start of each session), to the therapeutic work as a whole. Barkham terms this in-therapy, iterative uses of data as ‘personalisation’—distinct from the ‘precision’ tailoring of Layers 3 and 4.

Note, even at these highest layers of specificity, data still only ever gives indications of what might be of benefit to a client at a particular time, not what is. Client preferences, for instance, tell us what a particular client thinks will be helpful, but there are no guarantees that such practices are of benefit; ROM predicts when clients may most be ‘off track’, but there are still numerous sources of ‘error variance’ meaning that, in fact, some of these clients may be doing very well (what has been termed ‘paradoxical outcomes’). As we move up the layers, then, we may move from distal to proximal forms of evidence, less to more trustworthy, but even at the highest layer, we are only ever dealing with approximations. Hence, while higher layer data, where present, may deserve prioritisation, best practice may ultimately come through informing clinical work with data from across multiple layers.

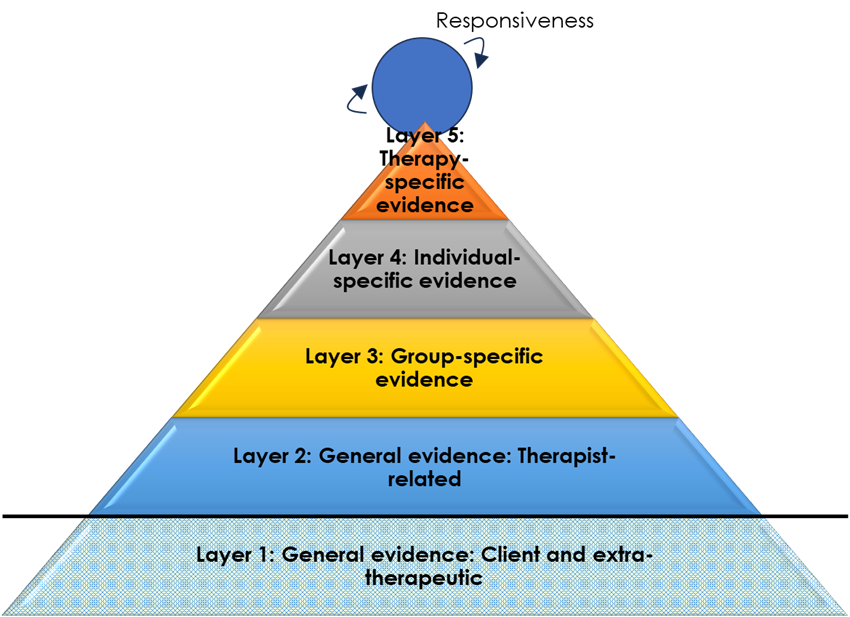
In fact, Layer 5 is probably not the highest and most specific layer of data usage to optimise benefits in therapy. At every moment of the therapeutic work, therapists will be striving to attune therapeutic practices to what they perceive—consciously or unconsciously—as beneficial or hindering to clients. A client seems to become animated, for instance, by being asked about their brother, and the therapist enquires further; a client glances away when the therapist asks about the psychotherapy relationship and the therapist seeks another way of addressing the here-and-now relationship. Stiles refers to this as therapist ‘responsiveness’, and this is represented as a spinning circle right at the top of the pyramid (Figure 4). Bill Stiles, in a personal communication, has written:

Representing responsiveness research as a (spinning?) circle (wheel? ball?) at the top seems to me to convey both the recursive feedback idea (circle, spinning) and the potentially high specificity (possibly millisecond-scale, e.g., responsive adjustments in mid-sentence due to facial expressions).

These five layers of evidence, then, segue into the moment-by-moment, ‘evidence based’ adjustments that therapists are constantly making throughout their work. And, as the highest layer, such responsiveness may be most proximal and attuned to what clients will find most helpful. Nevertheless, in the absence of such proximal information, each of the preceding layers will give valuable information about where best to start with clients. Moreover, as suggested in the previous paragraph, given the vagaries and potential errors inherent in each layer of data (including responsiveness: for instance, the therapist may misread the client’s reaction, or the client may be hiding it through deference), it is probably a combination of evidence from across the layers that is likely to be most beneficial in successfully guiding therapy.

Figure 4. Layers of Evidence Segueing into In-Session Responsiveness

Although each of these layers of evidence have the potential to inform therapeutic practice, different individuals, training programmes, or services may place emphasis on very different layers. For instance, in the IAPT model (Improving Access to Psychological Therapies, now NHS talking therapies), based on NICE guidelines, practice is nearly-exclusively drawn from evidence at Layer 3 (in particular, diagnoses-specific evidence), with little consideration for other layers (see Figure 5). Even responsiveness to the needs and wants to the individual client, during IAPT practice, tends to be subsumed to manualised, ‘evidence-based’ guidance.

NHS/IAPT Emphasis on Diagnosis-Specific Evidence

On the other hand, in approaches like Scott Miller’s feedback-informed therapy, there is a particular reliance on the most proximal evidence: the client’s immediate feedback through ROM (Layer 5), as well as a responsiveness to the particular client in the particular moment (Figure 6).

Figure 6. Feedback-Informed Emphasis on Proximal Data

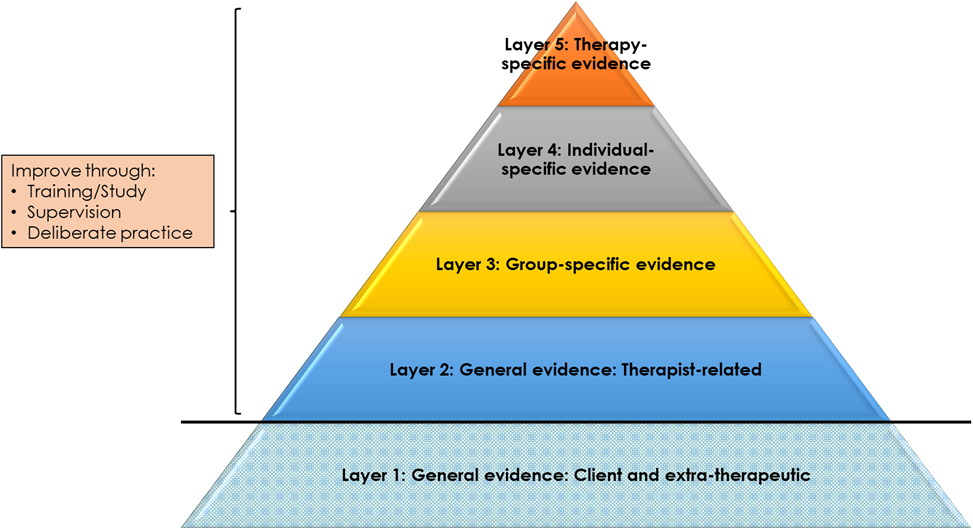
In contrast to Layer 1, Layers 2 to 5 provide opportunities for therapists to enhance their practice (Figure 7). This is in two respects. First, at a basic level, skills and competences can be developed in practices that have been shown to lead to beneficial outcomes. This is particularly Layer 2 general relationship factors (e.g., enhancing levels of empathy) and technique factors (e.g., developing skills in two-chair work). In addition, at a more meta-level, knowledge and competences can be developed in tailoring practices to group- (Layer 3), individual- (Layer 4), and therapy- (Layer 5) specific evidence. For instance, at Layer 5, trainees can be taught how to use ROM data to monitor and enhance therapeutic outcomes, particularly with ‘not on track’ clients. Such training may be based on informal guidance and feedback (e.g., through supervision) or, itself, may be evidence based: using data to feed back to trainees how they are doing on particular competences. A supervisor, for instance, might rate segments of their supervisee’s audio recordings, across multiple time points, on a practice adherence measure like the Person-Centred and Experiential Psychotherapy Rating Scale (PCEPS). This moves us into the realm of ‘deliberate practice’ and, indeed, a separate pyramid could be developed for the use of research in training: from the most general evidence about factors that improve practice to therapist-specific data on what an individual practitioner might do to improve their outcomes.

Figure 7. Opportunities to Develop Therapist Competences and Meta-Competences

In fact, Layer 1 probably does also offer opportunities for enhancing the beneficial effects of therapeutic work—perhaps to a great extent—though this is rarely the focus of study or training. Here, emphasis is on how clients might be empowered or enabled to develop skills in using therapy most effectively. A good example would be the ‘resource activation’ work of Christoph Flückiger and colleagues, which invites clients to draw on their own strengths and resources to ‘drive’ the therapeutic process. In addition, this is the layer at which therapists might be developing competences in social and political advocacy practices. Developing the ability, for instance, to challenge unjust organisational policies might help to address the psychological distress brought about by racial discrimination.

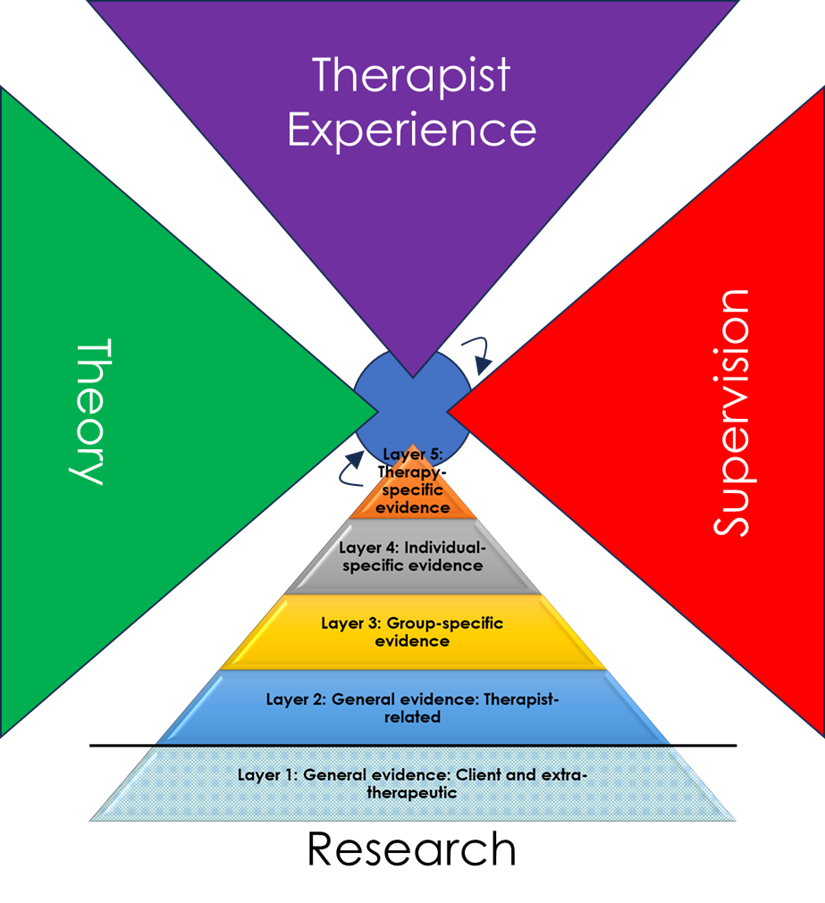
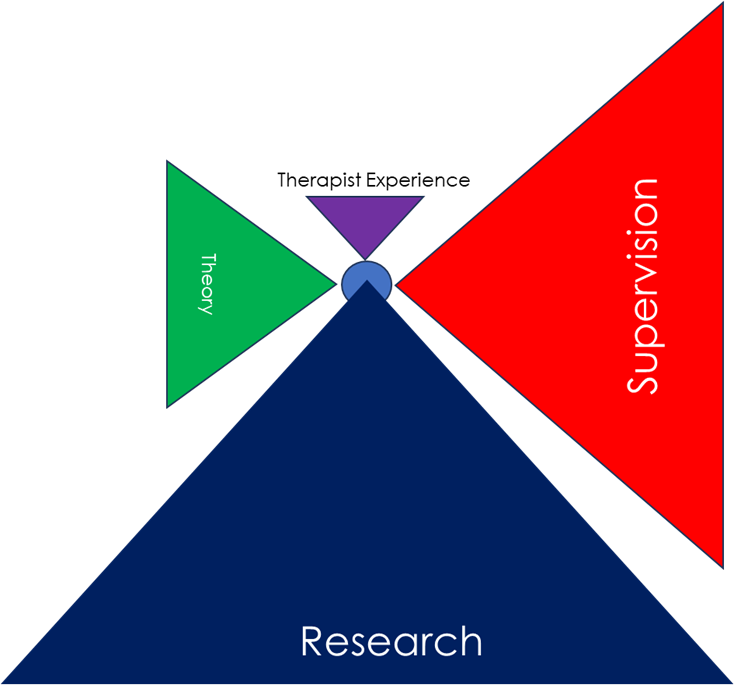
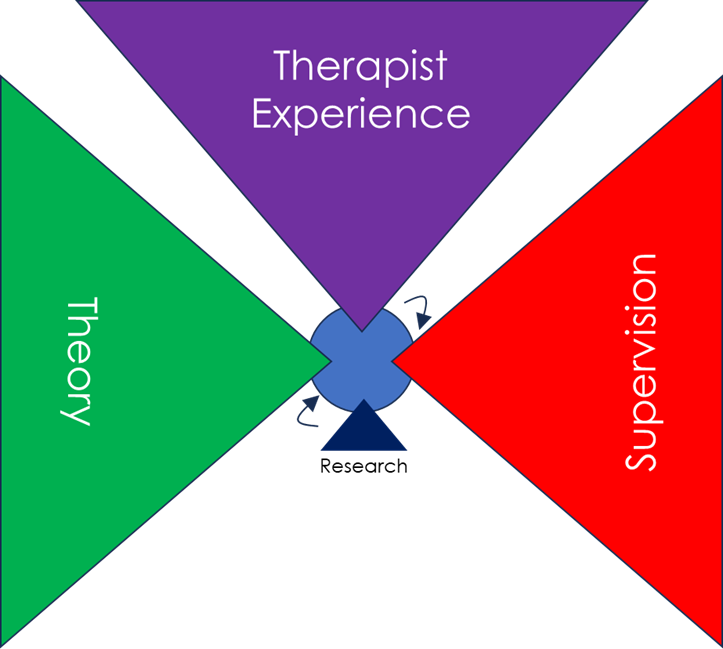
Of course, research evidence is not the only sources of guidance on how to practice. Therapists may also draw, for instance, from theory, their own experiences, and from their supervision work. These sources are likely to be interlinked in complex ways, but for simplicity sake we can present them as per Figure 8.

Figure 8. Multiple Sources of Guidance on Practice

And, as with the layers of evidence, different individuals, training programmes, or services may place emphasis on very different sources to guide practice. In NHS Talking Therapies, for instance, practice is primarily based on research evidence (Layer 3, diagnosis-specific) (see Figure 9). By contrast, in much of the counselling field, practice is primarily guided by theory, supervision, and the therapist’s own personal experiences—as well as responsiveness in the specific moment—with research evidence playing only a very minor role (Figure 10).

Figure 9. Sources of Practice in NHS Talking Therapies

Figure 10. Typical Sources of Practice in the Counselling Field

Again, one might argue that, in best practice, there is an openness to drawing fully from all potential sources.  

This pyramidal framework for drawing on research evidence is very different from the ‘hierarchy of evidence’ as used, for instance, in NICE clinical guidelines. While the latter ranks research according to its ‘objectivity’—placing randomised clinical trials and their meta-analyses at the top and expert opinion at the bottom—the present framework makes no assumptions about the relative worth of different methodologies. Qualitative research, for instance, may be a very powerful means of understanding what particular methods or practices are particularly helpful for particular groups of clients (Layer 3). Indeed, in this framework, the data that may be of most value to particular episodes of therapy—by being most proximal—is individualised ROM data: very different from the kind of generalised RCT data prioritised in the standard hierarchy of evidence.

Conclusions

When trying to make sense of the vast body of psychotherapy research evidence, there are many different ways of organising the research:

  • Different factors (therapist, client, etc)

  • Degree of ‘independence’/rigour of the research (the IAPT/NICE approach)

  • Effective treatments for different problems (again, the the IAPT/NICE approach)

  • Evidence for different therapeutic approaches overall

  • The proximity of the research evidence to the actual client and session (what is being proposed here)

Of course, there is no one right way, and these different organising principles can be combined in a wide variety of ways. For instance, the evidence at each layer of the present framework could then be organised by degree of independence of the research, or by different factors. However, each of these frameworks do prioritise and emphasise, even if implicitly, different elements of the research evidence. In the present one, there is as implicit privileging of data that is most proximal to the client—the ‘top’ of the pyramid. This can be seen as emerging from my own humanistic, existential, and phenomenological ‘ontology’ (theory of being) and ethics, which tends to reject the positivist assumption that the universe acts—and can be understood as acting—according to general, underlying mechanisms and laws. Rather, there is an emphasis here on ‘otherness’ and the irreducibility of human being. That is, that human beings’ lived-experiences can be unique, and that focusing on the unique and distinctive aspects of that experiencing is an important element—both ontologically and ethically—of understanding the whole.

Having said that, as Nicola Blunden points out in her comments below, the approach presented here is therapist-centred, in that it is a framework by which therapists can use the evidence. That is consistent with the target audience of my ‘facts are friendly’ book, but it raises the question of what a client-centred, or relationship-centred framework for making sense of the research findings would look like. Perhaps that would start with a greater focus on, and nuancing of, ‘Layer 1’ evidence: What can the client do with this to maximise their therapeutic outcomes? Nicola also raises the interesting point of whether a pyramid is still too hierarchical: would a target or spiral be a better representation of the potential use of data in therapy?

The pyramidal framework presented here is a way of organising research data to inform therapeutic practice. The pyramid builds, in layers, from the most general to the most specific evidence of what works—and is working—for an individual client. This framework does not negate a more factors-based taxonomy—indeed, it can incorporate it—but emphasises, instead, the relative proximity of different data sources to the actuality of each episode of clinical practice. Perhaps what is most useful about this framework is it provides a means of segueing from general and group-level research to individual-level research—and then, even, on to responsivity in moment-by-moment practice. This may allow a greater integration of research data into practice: research, here, is not something separate from what therapists generally do, but something spread on a continuum from the most general to the most specific. This framework is also a means of representing the way different sources of evidence may be weighted in different approaches, as well as the weighting of research evidence against other sources of clinical guidance. And while this framework does not indicate which sources (research or otherwise) should be prioritised, by mapping out possibilities in this way, it hints at the potential value of all. While this framework is a work in progress, it may be a way of organising and making sense of the research evidence that encourage a broader, more encompassing, and more pluralistic conceptualisation of all its uses.

Working with Client Preferences in Counselling and Psychotherapy

Mick Cooper, University of Roehampton, London; John C. Norcross, University of Scranton, PA, USA

Client preferences can be defined as the specific conditions and activities that clients want in their therapy. The literature suggests three main types of client preferences [1]. First are treatment preferences: the desires that clients have for specific types of intervention, like person-centred or psychodynamic. Second are preferences about the therapist. This is the kind of counsellor or psychotherapist that the client would like to work with; for instance, lesbian, Asian, or an older adult. Third are activity preferences: the specific actions that clients desire to engage in throughout the therapy process. This can include the frequency and format of therapy (for instance, online therapy), the methods and techniques to be used (for instance, two-chair work), the preferred topics to focus on (for instance, early childhood), and the therapist’s particular style (for instance, focusing on emotions).

In preference work, we can also distinguish between preference assessment—the identification of clients’ strong likes and dislikes—and preference accommodation—the therapist adjustment of their way of working to the client’s expressed desires [2].

There are both ethical and empirical reasons why therapists should concern themselves with client preferences. Research shows that clients are as much as 50% less likely to drop out of therapy when the treatment matches their preferences, and also show somewhat better outcomes. So, for instance, a client who wants a warm, supportive, client-led therapy style may be particularly likely to drop out—or show relatively poor outcomes—if they are given a highly directive and therapist-led CBT [1]. Ethically, preference assessment and accommodation can convey a deep respect for our clients and their ways of seeing their worlds: a core requirement of any ethical framework [e.g., 3]. It also means respecting our clients’ rights to be autonomous, self-governing agents; and recognising that they are not uniform, ‘machine-made’ products, but individualized beings with distinctive wants. Such honouring of difference is also important across cultures. A White male counsellor, for instance, who does not ask his female Pakistani client about her particular preferences may end up imposing European, ‘male’ assumptions on her. When we ask, therefore, we share power; we move away from a comparatively authoritarian, expert-led stance towards a more egalitarian and democratic one.

Addressing Common Concerns

Therapists, quite rightly, have a number of concerns about working with client preferences, and these are worth addressing up front.

‘Most of my clients don’t know what they want’

It’s certainly true that some clients don’t have strong preferences, particularly if they have not been in counselling or psychotherapy before. But preference work is not an all-or-nothing thing: it’s about gently and sensitively offering clients an opportunity to share their preferences, if and when they have them and would like to do so.

‘What clients want isn’t necessarily what they need’

That can be true. A client, for instance, might want warmth and reassurance from their therapist when, actually, what would help them is to learn to tolerate anxieties and tensions in interpersonal relationships. But, as we have seen, research shows that, overall, clients succeed better in therapy when they get the approach they want. Moreover, when therapists think that what a client requests will not prove helpful, then can then raise that concern with them. It’s not about handing over responsibility to clients, but working collaboratively with them—‘shared decision making’, as they call it in the medical field—to work out, together, the best way forward.

‘Clients preferences can change over the course of therapy’

 Yes, some do and some don’t (though our research shows that most client preferences are pretty stable over time). That means that assessing client preferences is not a ‘set-and-forget’ process. It’s often more tentative and recursive: opening up the discussion, trying things, and being willing to change the way of working if clients are not finding it helpful or want something else.

‘Does that mean I have to offer every therapeutic methods to every client I meet?’

No, we can only learn so many approaches, and we have to practice within our competencies. Thus, sometimes, working with client preferences means recognising that what they want is not what we can competently offer (and referral to another may be indicated). But, generally, it is much better that clients and therapists have that discussion early on, rather than discovering incompatibilities months into treatment.

‘I already have an intuitive sense of what my clients want, so why bother asking?’

Intuition is a valuable skill; but research shows, again and again, that therapists’ and clients’ perceptions of what is going on in therapy are often mismatched. For instance, one study found that, in about two-thirds of cases, clients and therapists had somewhat different views about the goals for therapy [4]. Moreover, there is a risk that therapists’ intuitive sense of what clients want are biased by the therapists’ own therapy preferences. Our research shows that there are quite large and systematic differences between what therapists and laypeople want, as clients [5].

‘I already work with clients’ preferences. I don’t need to do more’

Interestingly, in the medical field, doctors tend to think there’s more shared decision making going on than patients [6]. The difference may come down to power. If a doctor says, ‘Why don’t we try treatment X’, and a patient nods their head, the doctor may feel it’s a shared decision; but, for the patient, it may be more a case of compliance for fear of appearing ignorant or rude. Given that a similar power dynamic can exist in therapy—with research showing that client deference frequently occurs, even in person-centred approaches [7]—it behoves all therapists to reflect on their practice and think about how frequently they provide clients with opportunities to express their preferences. It may be less than we think.  

Assessing Client Preferences

So how should you go about assessing client preferences?

Almost certainly, the first step is a reflexive one: asking yourself, What is my scope of practice? That is, what are you (a) competent and (b) willing to offer to your clients? For instance, are you able and willing to offer transference interpretations, anxiety-management skills, or methods to discover meaning in life? What about individual, couple, group, or family therapy? Recognising what you can offer clients is essential in responding effectively to clients’ stated preferences—you will need to know whether what they ask for is something you can adopt or not.

Assessment of client preferences most commonly takes place at initial, or intake, appointments. It is probably best if this assessment takes place towards the end of that session—clients often come to therapy anxious, or with their own accounts that they want to offload—and it may be a few sessions before clients are ready to say something of what they prefer. We recommend that the clients’ treatment goals (the ‘where’) be established before ascertaining their preferences (the ‘how’).

 There are many ways that clients can be invited to express their preferences, for instance:

  •  What do you think that we can do here that might be helpful to you? Do you have any sense of what wouldn’t be helpful?

  • What would you like in our work together? What kind of preferences do you have?

  • Try this brief exercise. Close your eyes, breathe deeply a few times, and imagine in your mind’s eye what you would strongly like to happen in here. What would I ideally do? What would I not do?

  • Let’s think together about how you might get what you want from therapy. Which treatment method? What type of therapy relationship? What type of out-of-office activities: self-help, exercise, apps, and so on?’

 Assessment of client preferences can also take place before that intake meeting. For instance, on an initial phone conversation, a prospective therapist may ask about particular treatment preferences or preferences about the therapist to ensure there is a basic compatibility before moving forward. Scheduled review sessions are another point at which clients may be asked about their preferences, and whether the therapist’s methods and style seems to be of help. And, of course, throughout the therapy sessions there may be occasions where it is appropriate and helpful to discuss client preference: for instance, at the start of sessions, when the therapy is not progressing well, when there is an alliance rupture, or when the ending approaches. In fact, recursive assessment of preferences often becomes part of routine outcome monitoring.

Based on the research and our clinical experience [2], we offer several principles of good practice in preference assessment:

  • Focus on strong preferences—what clients might really want and really dislike—rather than milder or more moderate preferences; it’s the former where accommodation or non-accommodation is most likely to count.

  • Ask clients what worked and did not work in previous therapies, if they have had them. It’s often the most simple and natural way in to helping identify what might be helpful now.

  • ‘It’s the relationship, stupid’: preference assessment needs to be framed within the context of a respectful, warm, collaborative therapeutic relationship; if not, it may be little more than a sterile data gathering process.

  • Make it clear that asking about preferences is a normal part of counselling and psychotherapy. Clients may be surprised to be asked, and assume that therapy is like other, practitioner-led ‘treatments’.

  • Actively invite clients to share their preferences: given client deference (see above), it’s not enough just to assume that, if they have preferences, they’ll verbalize them.

  • Be part of the dialogue yourself: shared decision making means shared—you need to work with the client to help decide, together, what might be best for them.

  • Be confident: at its worst, preference assessment can communicate to clients that we don’t know how to help them, and that it’s their responsibility to decide. So the message we want to communicate to clients is, ‘We’ve got lots of ideas about how to help you, but we’re really interested in your ideas too. I am the expert on therapy and you are the expert on you.’

  • Suggest alternatives through ‘scaffolding’: clients can easily feel overwhelmed if they’re presented with a ‘blank sheet of paper’ and asked, ‘What do you want?’ Rather, it is often helpful to suggest 2 or 3 specific possibilities, for instance, ‘We could talk about your grandmother this session, or perhaps you would like to focus on your boyfriend?’

  • Don’t ‘overcook’ it: if clients do not have ideas about will help them, or seem reluctant to talk about it, then move on. You can come back to their preferences later on in the therapeutic process, if it seems appropriate.

  • Tailor the tailoring: some clients, some of the time, want to have their preferences assessed and accommodated; others, do not. Hence adjust the amount of preference work to the individual client—there is no one size fits all, even when it comes to the client’s preferences.

Through our research, we have developed a tool to assess strong client preferences, the Cooper-Norcross Inventory of Preferences (C-NIP) [8]. This measure, now translated into over ten languages and freely available for use digitally or on paper (see c-nip.net), invites clients to express their preferences for therapy along four dimensions: (a) Therapist directiveness vs Client directiveness, (b) Emotional intensity vs Emotional reserve, (c) Past orientation vs Present orientation, and (d) Warm Support vs Focused challenge. The measure takes clients about five minutes to complete and can be immediately scored in session to indicate whether the client has strong preferences on any of these dimensions. This then serves as the basis for discussion about how the therapist and client can work together. Our research suggests that clients generally find the C-NIP helpful, supporting their ability to articulate how they want to proceed in treatment. And, they say, it feels good to be asked.

Working with Client Preferences in Therapy

Once clients’ preferences are assessed, there is the question of how they are accommodated—or not—into the therapeutic work. In our book, Personalizing Psychotherapy, we suggest four possibilities: adopt, adapt, alternative, or another.

Adopt means that we integrate the client’s strong preferences, pretty much as they are, into treatment—bearing in mind, of course, that these preferences (and our scope of practice) may change over time.

Adapt is offering something along the lines of what the client wanted, but adjusted to take into account our own views of what might prove most effective, the research evidence, ethical considerations, or the limits of our own scope of practice. In the case of Hamza, for example, there was a small but significant mismatch between what he wanted from treatment and the therapist’s (Mick’s) understanding of what might be most helpful for him:

Hamza presented with high levels of depression and anxiety and was becoming increasingly withdrawn from his college and social environment. The therapist view, based on an understanding of core behavioural principles, was that Hamza needed to be encouraged to get out and re-engage with his world. The more he withdrew, the more anxious and isolated he became. Hamza sensed this pattern as well. However, he also indicated that, based on a previous episode of CBT, it was unhelpful for him to be told by a therapist, ‘If you don’t do what I’m suggesting, you’re not going to get better.’ He related that it left him feeling guilty, ashamed, and even less confident to go out into the world. The adaptation challenge was to find methods of communicating to Hamza that he could change his behaviours, without implying that he was ‘bad’ or ‘wrong’ if he did not. A delicate balance needed to be struck between helping Hamza own some responsibility and, at the same time, avoiding his strong dislike of feeling blamed. [2]

 The third option is to respectfully propose alternatives to patients’ strong likes and dislikes. This would be when we believe their preferences will not be most suited to the particular context, or when we do not think it will produce the desired results. Just because clients want something does not mean that we should automatically provide it. Ethical, legal, and clinical constraints still bind us to responsible and effective practice. In some cases, for instance, clients may be unconsciously trying to recreate problematic relationship or to test the therapy’s frame. Three ‘E’s may be helpful when proposing alternatives to clients [2]:

  • Explain your reasoning for not accommodating or adapting.

  • Empathize with probable patient disappointment.

  • Educate the client about the proposed alternative, so that they understand why it is being proposed.

When a client’s strong preferences prove congruent with the research evidence and best practices, but not our own scope of practice, then referral to another becomes a strong possibility [2]. This is a practice that students often receive little training in, but it is an essential competence, given our inevitable limits and our desire for clients to have the best therapy possible. Some helpful pointers for therapists may be:

  • Accept your limits as a clinician: see onward referral as a sign of your commitment to your clients’ mental health rather than as an indication of your failings.

  • Be aware that some clients may experience onward referral as a sign of rejection or an indication that their mental health problems are incurable. Make clear that it is due to your competency boundaries as a therapist, rather than their failure as a patient.

  • Refer onwards in a collaborative way with clients so that it is experienced as a shared and empowering experience, rather than as something imposed on them.

  • Provide concrete suggestions and specific sources in mind, as opposed to vague referrals to other services. This may mean being aware of other resources in your community—for instance, low-cost CBT practitioners or substance misuse programmes—before having these discussions with clients.

  • Obtain proper permission or releases so that you can communicate with other clinicians or clinics; that will ensure continuity of care and help the treatment personalization forward. [2] 

Conclusion

Assessing and accommodating clients’ preferences constitutes a complex, nuanced set of practices and interactions that evolve over the course of therapy. It is, at heart, about creating a more egalitarian, empowering, and responsive relationship that enables clients to use counselling and psychotherapy most effectively. Both research and practice attest to the success of preference work.

But there is still much more to learn. Which clients in which situations, for instance, are most (and least) benefitted by preference work? How can we most effectively help clients articulate their preferences? Answering these kinds of questions is part of a wider movement towards personalised care, in which our clients are treated as more than just instances of a general class (for instance, ‘depressives’ or ‘borderline types’), but as unique human beings with specific and individual desires. When we ask clients about their preferences, as with Buber’s ‘I–Thou attitude’ [9], we affirm them as agentic participants or partners, who have the power—and right—to direct their own process of change. This is certainly not the only means of conveying such valuing and respect to our clients, but it becomes an integral part of a deeply affirming, empowering relationship. 

Further Reading

Our book, Personalizing Psychotherapy: Assessing and Accommodating Client Preferences, is now available from APA. For UK readers, a 40% discount is available for the book with free standard delivery. Please go to www.eurospanbookstore.com/personalizing-psychotherapy.html and use the ‘code Psychotherapy40’. This offer valid until at least 31/4/21 and open to customers based in the UK, Europe, Middle East, and Africa.

References

1. Swift, J.K., et al., Preferences, in Psychotherapy relationships that work, J.C. Norcross & B. E. Wampold, Editors 2019, Oxford University: NY. p. 157-187.

2. Norcross, J.C. and M. Cooper, Personalizing psychotherapy: Assessing and accommodating client preferences2021, Washington: APA.

3. British Association for Counselling and Psychotherapy, Ethical framework for the counselling professions, 2018, BACP: Lutterworth.

4. Swift, J. and J. Callahan, Early psychotherapy processes: An examination of client and trainee clinician perspective convergence. Clinical psychology & psychotherapy, 2009. 16(3): p. 228-236.

5. Cooper, M., et al., Psychotherapy preferences of laypersons and mental health professionals: Whose therapy is it? Psychotherapy, 2019. 56: p. 205-216.

6. The Health Foundation, Helping people share decision making, 2012, The Health Foundation: London.

7.  Rennie, D.L., Clients' deference in psychotherapy. Journal of Counseling Psychology, 1994. 41(4): p. 427-437.

8. Cooper, M. and J.C. Norcross, A Brief, Multidimensional Measure of Clients' Therapy Preferences: The Cooper-Norcross Inventory of Preferences (C-NIP). International Journal of Clinical and Health Psychology, 2016. 16(1): p. 87-98.

9. Buber, M., I and Thou. 2nd ed1958, Edinburgh: T & T Clark Ltd.

[Spanish translation of this blog post]